


Ilizarov Hip Reconstruction Surgery

Home / Treatments / Ilizarov Hip Reconstruction Surgery

Ilizarov Hip Reconstruction Surgery

Hip deformity, chronic dislocation, and avascular necrosis leave young patients facing a difficult choice – accept disability or undergo a total hip replacement that may need revision within two decades. Ilizarov Hip Reconstruction offers a third path. Using a circular external fixator and a staged osteotomy technique, Dr. Divya Ahuja corrects severe hip deformities, restores limb alignment, and preserves the natural joint without an implant.

Home/Treatments/Ilizarov Hip Reconstruction Surgery
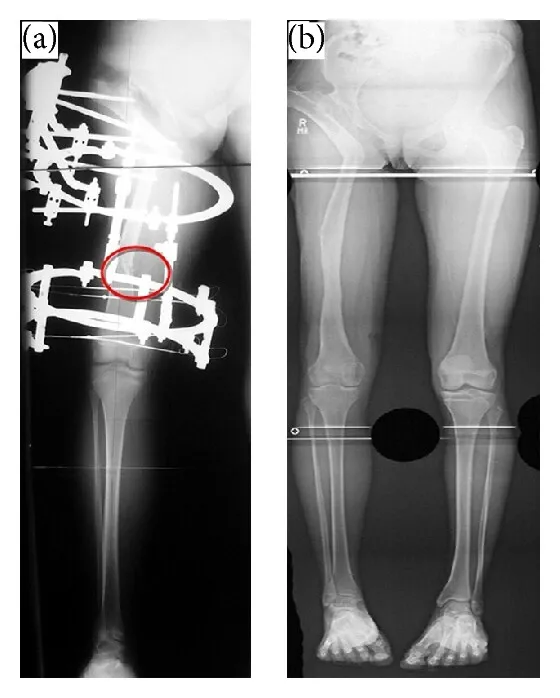
X-ray showing leg with external fixator before treatment and corrected, aligned legs after

What Is Ilizarov Hip Reconstruction?

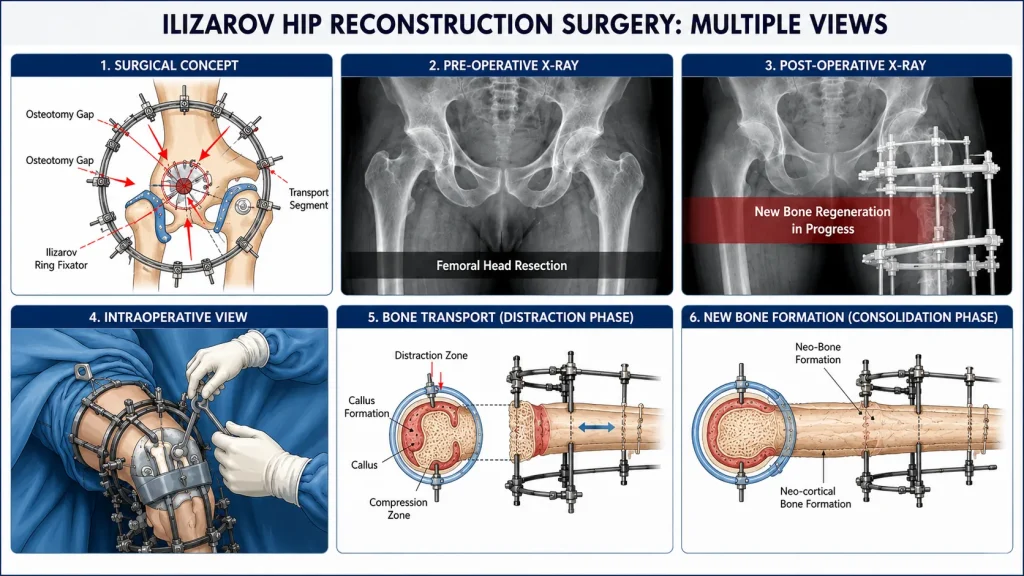
Ilizarov Hip Reconstruction is a specialised orthopaedic procedure that uses the Ilizarov external fixator – a circular frame of rings, wires, and threaded rods – to gradually correct the position, length, and alignment of a severely damaged hip.

The technique works through distraction osteogenesis: when bone segments are slowly drawn apart at a controlled rate of approximately 1 mm per day, the body generates new bone tissue to fill the gap. This biological principle, pioneered by Soviet surgeon Gavriil Ilizarov, allows complex deformities to be corrected without removing or replacing the joint.

For Ilizarov hip reconstruction specifically, the procedure relies on a double osteotomy. A proximal cut near the ischial tuberosity creates a pelvic support mechanism and corrects valgus deformity. A second, more distal osteotomy addresses the leg length discrepancy. Though the bone appears angulated on X-ray during treatment, the mechanical load-bearing axis is centralised, and the limb looks straight from the outside.

To understand how the Ilizarov technique is used across different bone conditions, visit the Ilizarov Surgery overview.

Conditions Treated with Ilizarov Hip Reconstruction

Ilizarov Hip Reconstruction is indicated for complex hip conditions where conventional surgical approaches are either inadequate or inappropriate for young, active patients.

  • Developmental Dysplasia of the Hip (DDH): Congenital hip instability with proximal femoral migration, limb shortening, and the characteristic Trendelenburg limp. DDH is the most common indication for this procedure.
  • Neglected Hip Dislocations: Long-standing dislocations that were untreated in childhood, where the femoral head has migrated and the surrounding soft tissue has adapted to the abnormal position.
  • Sequelae of Childhood Septic Arthritis: Infection in infancy or early childhood can destroy the femoral head, leaving the adult patient with a flail hip and significant leg length discrepancy.
  • Avascular Necrosis (AVN): In selected cases, realigning the hip reduces mechanical stress on the necrotic segment and may slow progression, preserving the joint longer than without surgery.
  • Post-Traumatic Hip Deformities: Fractures that healed with malalignment, causing pain, abnormal gait, and limb length imbalance that cannot be addressed by physiotherapy alone.
  • Tuberculous or Pyogenic Arthritis Sequelae: Hip destruction following bone tuberculosis or infective arthritis in childhood is a significant cause of hip instability in India.

These conditions share a critical feature – the patient is too young for total hip replacement, and the hip cannot be left as is. Ilizarov Hip Reconstruction is often the only method that simultaneously corrects deformity, restores limb length, supports the pelvis, and preserves the biological joint.

Where limb length difference is a primary concern alongside hip reconstruction, also see Limb Lengthening Surgery and Limb Length Discrepancy.

Ilizarov Hip Reconstruction vs Total Hip Replacement

Many patients under 40 are told that total hip replacement is their only option. This advice, while sometimes accurate, overlooks an important biological fact: a hip implant has a functional lifespan of 15 to 20 years. A 25-year-old who receives a total hip replacement will almost certainly need a revision surgery – a more complex and riskier procedure – at least once in their lifetime.

Ilizarov Hip Reconstruction and total hip replacement serve different patient profiles and solve different problems.


Ilizarov Hip Reconstruction

Total Hip Replacement

Ideal age group

Adolescents and young adults (15–40)

Usually 50 and above

Primary goal

Preserve natural joints, correct deformity

Replace the damaged joint entirely

Revision risk

Low

High in younger patients

Limb length correction

Yes – an integral part of the procedure

Limited correction possible

Frame/recovery duration

6–12 months with frame

3–6 months post-surgery

Best suited for

DDH, dislocation, infection sequelae

End-stage arthritis, elderly patients

For patients with end-stage arthritis at an older age, total hip replacement remains the right choice. The decision depends on age, diagnosis, bone stock quality, and long-term functional goals – all evaluated during a pre-operative consultation with Dr Divya Ahuja.

How Is Ilizarov Hip Reconstruction Performed?

Timeline showing the major stages involved in Ilizarov Hip Reconstruction surgery.

Dr. Divya Ahuja follows a structured protocol for each case, with pre-operative planning driving every surgical decision.

Step 1 – Pre-operative planning: Full-length standing X-rays, CT scans, and where indicated, MRI map the deformity in precise detail. Limb length discrepancy, femoral neck angle, and pelvic obliquity are measured before surgery begins.

Step 2 – Double osteotomy: Under general anaesthesia, two controlled bone cuts are made in the femur. The proximal osteotomy near the ischial tuberosity creates a pelvic support mechanism. The distal osteotomy corrects valgus deformity and opens space for lengthening.

Step 3 – Frame application: The Ilizarov circular external fixator is assembled around the hip, pelvis, and femur using threaded half-pins and tensioned wires. The frame holds each bone segment precisely.

Step 4 – Distraction phase: Daily adjustments of approximately 1 mm begin 5 to 7 days after surgery. The distraction gap widens gradually, stimulating new bone formation – the same principle used in Bone Transport for large bone defects.

Step 5 – Consolidation: Once the correction target is reached, adjustments stop and the new bone consolidates. Serial X-rays confirm bridging callus and progressive union.

Step 6 – Frame removal: The fixator is removed as a minor procedure under anaesthesia once consolidation is confirmed, typically 4 to 8 months after surgery. Physiotherapy continues after removal to rebuild strength.

Preparing for Surgery

Patients who smoke must stop at least 6 weeks before surgery. Nicotine significantly impairs bone healing, delays consolidation, and increases pin site infection risk. Blood sugar, nutrition status, and any active infections should also be optimised before the procedure to support the best possible outcome.

Pin Site Care and Managing Complications

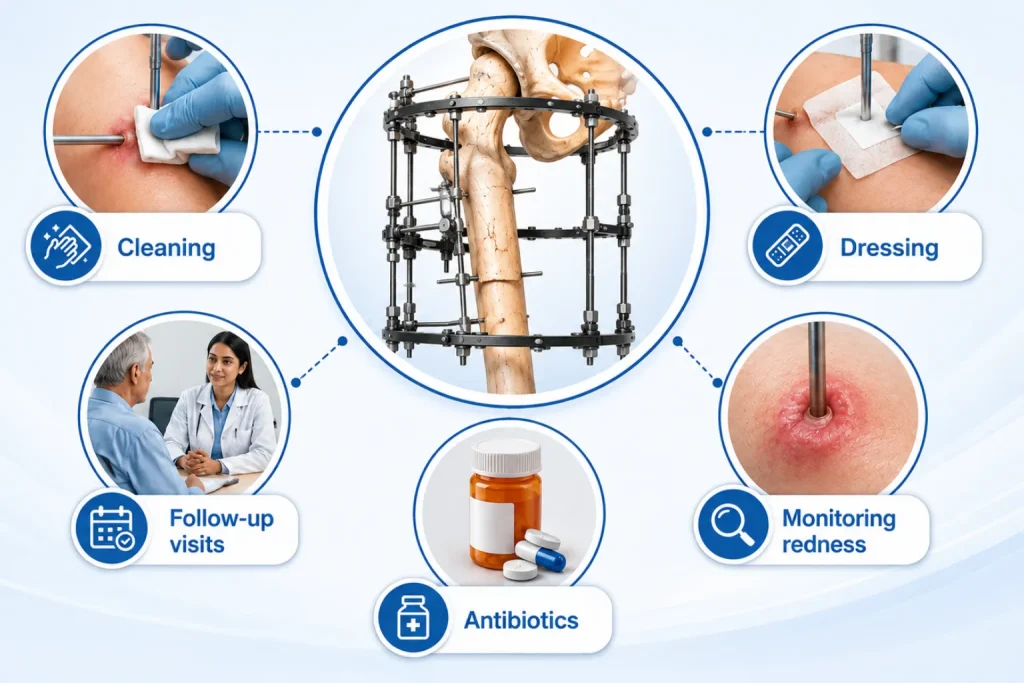
Pin site infection is the most common complication across all Ilizarov fixator surgeries, occurring in approximately 10 to 15% of cases. The majority are superficial and respond quickly to oral antibiotics and local wound care. Deep pin site infections requiring removal of a specific wire or additional intervention are uncommon when hygiene protocols are followed consistently throughout the frame period.

Other possible complications include:

  • Knee stiffness from prolonged immobilisation, addressed with early physiotherapy
  • Nerve irritation near pin entry sites is usually temporary
  • Delayed consolidation, particularly in patients who smoke, have poor nutrition, or are diabetic
  • Temporary increase in pain during the active distraction phase

Patients who have a background of Bone Infection or prior Nonunion are monitored more closely throughout the frame period, as their risk profile is slightly elevated.

What Published Studies Report

Peer-reviewed studies consistently report good-to-excellent outcomes in 85 to 95% of patients undergoing Ilizarov Hip Reconstruction. Research from AIIMS New Delhi, the Aga Khan University, and other South Asian institutions confirms that Harris Hip Scores improve substantially – from a mean preoperative score of approximately 56 to around 84 at five-year follow-up – across patients with DDH, septic arthritis sequelae, and post-traumatic deformities.

Key outcomes observed in published data:

  • The procedure aims to reduce the Trendelenburg limp, although the degree of improvement varies from patient to patient.
  • Limb length discrepancy corrected to within 1 cm in the majority of cases
  • Knee alignment improved concurrently owing to the distal osteotomy
  • No patient in medium-term studies (5 to 7 years) required subsequent hip replacement

Young patients aged 15 to 35 show the strongest bone remodelling response. Consistent physiotherapy, pin site discipline, and regular follow-up are the key variables that separate excellent outcomes from average ones.

Recovery After Ilizarov Hip Reconstruction

Recovery has two distinct phases: the active treatment phase with the frame in place, and the rehabilitation phase following removal.

During the frame period (4–8 months):

  • Physiotherapy begins within the first week of surgery to maintain knee and ankle mobility
  • Walking with a walker or crutches is encouraged from early on – weight bearing stimulates bone healing and prevents stiffness
  • Pin sites require daily cleaning with an antiseptic solution; a pin site infection kit is provided at discharge
  • Clinic visits every 3 to 4 weeks for X-rays and frame adjustment checks
  • Showering is possible with proper pin site protection; most patients manage daily hygiene independently within the first month

After frame removal:

  • Physiotherapy continues to rebuild hip abductors, quadriceps, and core strength
  • Most patients resume daily activities – including light work and walking without aids – within 6 months of frame removal
  • Full recovery, including walking without a noticeable limp, is typically achieved within 10 to 14 months of the original surgery

The Trendelenburg gait resolves in the large majority of patients as the hip stabilises and abductor muscle strength returns over 6 to 12 months.

Cost of Ilizarov Hip Reconstruction in India / Mumbai

India offers world-class Ilizarov Hip Reconstruction at a fraction of what the same procedure costs in Western countries.

  • Mumbai (typical range): INR 3.5 to 6.5 lakh, depending on case complexity, fixator duration, and hospital tier
  • Frame removal: A separate minor procedure costing approximately INR 20,000 to 60,000 after consolidation
  • International comparison: The equivalent procedure costs three to four times more in the US or UK
  • Insurance: Covered under most major Indian health insurance plans when performed for deformity correction or post-traumatic reconstruction. Cosmetic height augmentation is excluded.

Patients from Bangladesh, Sri Lanka, Gulf countries, and parts of Africa regularly travel to Mumbai for this procedure. Dr. Divya Ahuja’s team assists international patients with pre-arrival clinical planning, surgeon reports for medical visa applications, and long-term remote follow-up after they return home.

About the Treating Surgeon

Dr. Divya Ahuja is a Mumbai-based orthopaedic surgeon with over 20 years of focused experience in the Ilizarov technique, complex limb reconstruction, and deformity correction. He completed advanced training in Ilizarov surgery and serves as a faculty member at national and international Ilizarov workshops, teaching the technique to surgeons across India.

His clinical experience includes more than 1,000 bone and joint deformity surgeries, with a substantial subset being Ilizarov hip reconstructions for DDH, childhood infection sequelae, post-traumatic deformities, and avascular necrosis. Beyond the hip, he manages the full spectrum of limb and deformity conditions, including Bow Leg Correction, Knock Knees, High Tibial Osteotomy, and Foot Deformity correction.

To learn more about his training, publications, and clinical background, visit the About Dr. Divya Ahuja or Book an Appointment directly.

Frequently Asked Questions

A joint-preserving procedure using a circular external fixator and double femoral osteotomy to correct hip deformity, restore limb alignment, and improve walking without replacing the natural hip joint.

Developmental dysplasia of the hip, neglected dislocations, childhood septic arthritis sequelae, avascular necrosis, and post-traumatic hip deformities – primarily in adolescents and young adults who are unsuitable for total hip replacement.

The frame is worn for 4 to 8 months. Full recovery – including walking without a noticeable limp – typically takes 10 to 14 months from the date of surgery.

Some discomfort is expected during the distraction phase, but is managed with medications. Most patients find it tolerable after the first week, particularly once walking with the frame begins.

Published studies report good-to-excellent outcomes in 85 to 95% of patients, with significant Harris Hip Score improvement and resolution of Trendelenburg gait in over 80% of cases.

In Mumbai, the procedure typically costs INR 3.5 to 6.5 lakh, depending on complexity. This is three to four times more affordable than equivalent treatment in the US or UK.

Yes, and it is actively encouraged. Walking with a walker stimulates bone healing, prevents knee stiffness, and speeds recovery. Weight bearing is increased gradually under Dr. Ahuja’s supervision.

Frame removal is a minor procedure performed under anaesthesia or sedation once X-rays confirm full bone consolidation – usually 4 to 8 months after the original surgery.

Smokers must stop at least 6 weeks before the procedure. Nicotine impairs bone healing, delays consolidation in the distraction gap, and significantly increases the risk of pin site infections.

Ilizarov reconstruction preserves the natural joint and corrects deformity – best for patients under 40. Hip replacement removes the joint entirely and is better suited for older patients with end-stage arthritis.

X-ray showing leg with external fixator before treatment and corrected, aligned legs after