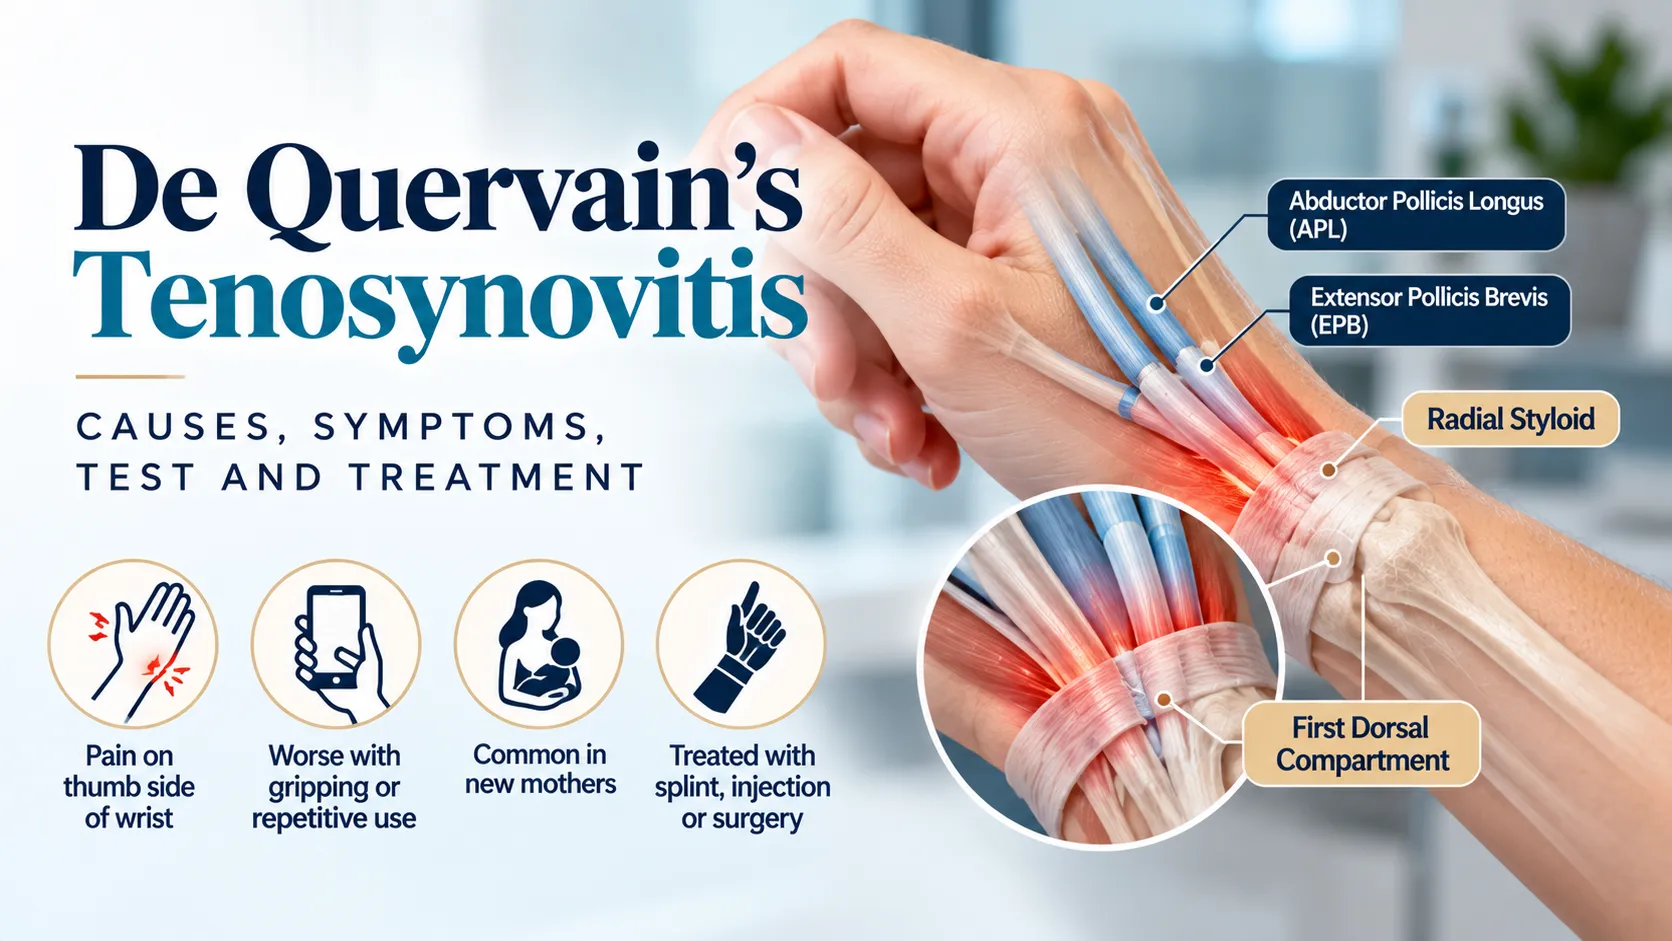
Quick Answer: De Quervain’s tenosynovitis is a painful condition affecting two tendons on the thumb side of the wrist, the abductor pollicis longus (APL) and extensor pollicis brevis (EPB). These tendons pass through a narrow tunnel called the first dorsal compartment. When the tendons and their covering sheath become thickened and irritated, gliding becomes painful. It is common in new mothers, people who use their thumbs repeatedly, heavy mobile phone users, and women between 30 and 50. Symptoms include pain and swelling near the base of the thumb, pain while gripping or lifting, and a catching feeling during thumb movement. Diagnosis is clinical, often confirmed by the Finkelstein test. Most cases improve with a thumb spica splint, activity modification, anti-inflammatory medicines, and a corticosteroid injection. Surgery to release the tendon tunnel is needed only when symptoms persist despite these measures.
Pain on the thumb side of the wrist that sharpens every time you lift your baby, grip a cup, or type on your phone is a very common complaint in orthopedic clinics. In many cases, the cause is De Quervain’s tenosynovitis, also called De Quervain’s disease, De Quervain syndrome, or simply DQ. It is named after Fritz de Quervain, the Swiss surgeon who first described it in 1895.
This article is written from the clinical perspective of Dr. Divya Ahuja at deformity.co.in, a Mumbai-based orthopedic and Ilizarov surgeon. It explains what De Quervain’s tenosynovitis is, why it happens, how to recognise it, and how it is treated, from simple splinting to surgical release.
What is De Quervain’s Tenosynovitis?
Tendons are strong cords that connect muscles to bone. Many tendons in the hand and wrist travel through smooth, slippery sheaths that let them glide easily. Tenosynovitis means irritation of a tendon and its surrounding sheath.
In De Quervain’s tenosynovitis, two thumb tendons are affected:
- Abductor pollicis longus (APL), which moves the thumb away from the hand
- Extensor pollicis brevis (EPB), which straightens the base of the thumb
These tendons run side by side along the thumb side of the wrist. They pass through a tight tunnel over a bony bump called the radial styloid. This tunnel is known as the first dorsal compartment. When the sheath thickens, the tendons rub against the tunnel walls with every thumb movement, causing pain and swelling.
Modern research shows that the problem is often more about thickening and degeneration than true inflammation. This is why doctors sometimes call it De Quervain’s tendinosis.
Anatomy of the Thumb Side of the Wrist

The wrist has six tunnels on its back surface, called dorsal compartments, that carry the extensor tendons. The first dorsal compartment sits on the thumb side and contains the APL and EPB tendons.
Important features include:
- The radial styloid, a bony bump at the end of the forearm bone on the thumb side
- The extensor retinaculum, a strong band of tissue that forms the roof of the tunnel
- Frequent anatomical variations, such as multiple slips of the APL tendon or a separate sub-tunnel for the EPB
These variations matter during treatment. A separate sub-compartment can explain why some patients don’t respond fully to an injection and why surgeons must check carefully during release surgery.
Causes and Risk Factors
De Quervain’s tenosynovitis usually develops from repeated thumb and wrist movements, especially gripping, pinching, and moving the wrist toward the little finger while the thumb is held.
Common causes and risk factors include:
- New motherhood, from repeatedly lifting a baby with the thumbs spread. This is why it is often called “mommy thumb”
- Pregnancy and breastfeeding, due to hormonal fluid changes
- Heavy mobile phone and tablet use, especially texting with the thumb
- Repetitive work such as typing, cooking, cutting vegetables, sewing, gardening, and assembly work
- Sports such as badminton, tennis, golf, and racquet games
- Female sex, especially between 30 and 50 years of age
- Inflammatory conditions such as rheumatoid arthritis
- Diabetes, which makes tendon sheaths more prone to thickening
- A direct injury to the wrist or an old wrist fracture
Symptoms of De Quervain’s Tenosynovitis

Symptoms often start gradually but can appear suddenly after a period of heavy hand use. Typical symptoms include:
- Pain on the thumb side of the wrist, near the base of the thumb
- Pain that worsens when gripping, pinching, twisting, or lifting
- Swelling over the radial styloid, sometimes with a small firm lump
- A catching or snapping feeling when moving the thumb
- Difficulty lifting a baby, opening jars, holding a cup, or turning a key
- Pain that spreads up the forearm or down into the thumb
- Tenderness when pressing over the tendon tunnel
Symptoms can affect one or both wrists, and the dominant hand is affected more often.
How De Quervain’s Tenosynovitis Is Diagnosed
Clinical Examination
Doctors usually make the diagnosis in the clinic. The doctor asks about your daily activities, work, hand use, pregnancy or childcare, and any injury. The examination checks for tenderness, swelling, and pain over the first dorsal compartment.
The Finkelstein Test
The most common test is the Finkelstein test. You tuck your thumb into your palm, close your fingers over it, and gently tilt your wrist toward the little finger. Sharp pain along the thumb side of the wrist strongly suggests De Quervain’s tenosynovitis. A related version, the Eichhoff test, is also widely used.
Imaging
Most patients do not need scans. Imaging is used when the diagnosis is unclear:
- X-rays to rule out arthritis at the base of the thumb, old fractures, or bony problems
- Ultrasound to show tendon sheath thickening, fluid, and separate sub-compartments
- MRI in rare cases where other wrist conditions need to be excluded
Conditions That Can Mimic De Quervain’s
Pain at the base of the thumb or the thumb side of the wrist has several possible causes. Correct diagnosis matters because treatment differs.
| Condition | Key Features | Typical Test |
|---|---|---|
| De Quervain’s tenosynovitis | Pain over radial styloid, worse with thumb movement | Finkelstein test |
| Thumb base (CMC) arthritis | Pain deeper at thumb base, grinding, older age | X-ray, grind test |
| Scaphoid fracture | Pain in the snuffbox after a fall | X-ray, MRI |
| Intersection syndrome | Pain and creaking higher up the forearm | Clinical, ultrasound |
| Wartenberg’s syndrome | Burning or tingling over back of thumb | Clinical, nerve tests |
| Ganglion cyst | Smooth, soft lump near the wrist | Ultrasound |
Treatment of De Quervain’s Tenosynovitis
The aim of treatment is to calm the irritated tendons and reduce the friction inside the tunnel. Most patients recover without surgery.
Activity Modification
Reducing the movements that trigger pain is the first and most important step:
- Avoid repeated pinching, gripping, and wrist twisting
- Change how you lift your baby, scooping with your forearms instead of the thumbs
- Take regular breaks from phone use, and switch to voice typing or using other fingers
- Use larger-handled tools and kitchen utensils to reduce grip force
- Keep the wrist in a neutral position while working at a computer
Thumb Spica Splint
A thumb spica splint, also called a DQ splint or De Quervain’s brace, holds the thumb and wrist still so the tendons can rest. It is usually worn for four to six weeks, often day and night at first. Splinting works best when started early.
Ice and Medicines
- Ice packs for 10 to 15 minutes several times a day reduce pain and swelling
- Short courses of anti-inflammatory medicines help ease pain, under medical advice
- Topical anti-inflammatory gels may be used over the painful area
Corticosteroid Injection
A corticosteroid injection into the tendon sheath is one of the most effective treatments. It reduces swelling of the sheath and often brings relief within a few days to weeks. A large share of patients improve after one injection, and some need a second. Injections done under ultrasound imaging can improve accuracy, especially when a separate EPB sub-compartment is present.
Possible side effects include temporary pain flare, skin thinning, and lightening of skin colour at the injection site. Repeated injections are avoided because they may weaken tendons.
Physiotherapy
Once pain settles, a physiotherapist or hand therapist may recommend:
- Gentle thumb and wrist range-of-motion exercises
- Gradual strengthening of the thumb and forearm muscles
- Tendon gliding exercises
- Kinesiology taping for support during activity
- Ergonomic training for work and childcare
When is Surgery Needed?
Surgery is considered when symptoms continue for several months despite splinting, activity changes, and one or two injections. The operation is called De Quervain’s release or first dorsal compartment release.
What Happens During De Quervain’s Release
- It is usually performed as a day-care procedure under local or regional anaesthesia
- A small incision is made over the thumb side of the wrist
- The roof of the first dorsal compartment is carefully opened to give the tendons more room
- The surgeon checks for and releases any separate sub-compartment
- A small sensory nerve branch near the tunnel, the superficial radial nerve, is carefully protected
Recovery After Surgery
- Stitches are removed in about 10 to 14 days
- Light hand use usually begins within a few days
- Most patients return to normal activities in four to six weeks
- Full strength may take two to three months
- The small scar usually fades well over time
Possible complications are uncommon but include tenderness around the scar, numbness from irritation of the nerve branch, tendon slipping out of place, and persistent symptoms if a sub-compartment is missed.
De Quervain’s Tenosynovitis in New Mothers
New mothers form one of the largest groups affected by De Quervain’s. Hormonal changes during pregnancy and breastfeeding, combined with repeated lifting of the baby with the thumbs spread wide, overload the tendons. The good news is that many cases settle within a few months as breastfeeding ends and hormone levels return to normal. Splinting and lifting technique changes help a great deal in the meantime. A corticosteroid injection can be given safely during breastfeeding when needed, after discussion with your doctor.
Self-Care Tips for Thumb and Wrist Pain
- Rest the thumb from painful activities as much as possible
- Wear your thumb spica splint as advised
- Apply ice after periods of heavy hand use
- Lift with your palms and forearms rather than your thumbs
- Use voice typing and hold your phone with both hands
- Stretch your forearm and wrist gently throughout the day
- Return to heavy activities gradually once pain improves
When to See an Orthopedic Surgeon
Consult an orthopedic surgeon if you have:
- Thumb-side wrist pain lasting more than two to three weeks
- Pain that affects childcare, work, or sleep
- Visible swelling or a lump over the thumb side of the wrist
- Catching or snapping during thumb movement
- No improvement despite rest and a splint
- Wrist pain after a fall, which may be a fracture rather than tendon irritation
Dr. Divya Ahuja, MS Ortho, is a Mumbai-based orthopedic and Ilizarov surgeon with over 15 years of experience in musculoskeletal care. His practice at the Center for Limb Lengthening and Reconstruction, Mangal Anand Hospital, Chembur, offers evaluation of thumb and wrist pain, accurate diagnosis, splinting, corticosteroid injections, and timely referral to a hand surgery specialist when surgical release is required. For a consultation with an experienced orthopedic surgeon in Mumbai, you can book online or visit the clinic at Chembur, Thane, Dadar, Vashi, Navi Mumbai, or Tilak Nagar.
Conclusion
De Quervain’s tenosynovitis is a common and very treatable cause of thumb-side wrist pain. Early rest, a good thumb splint, smart changes in how you use your hands, and a well-placed injection resolve most cases without surgery. When symptoms persist, a simple release procedure gives reliable long-term relief. If thumb and wrist pain is affecting your work, childcare, or daily life, consult Dr. Divya Ahuja for a clear diagnosis and a treatment plan suited to you.
Reviewed by Dr. Divya Ahuja, MS Ortho, Consultant Orthopedic and Ilizarov Surgeon, Center for Limb Lengthening and Reconstruction, Mangal Anand Hospital, Chembur, Mumbai.
Frequently Asked Questions (FAQs)
What is De Quervain’s tenosynovitis?
De Quervain’s tenosynovitis is a painful condition of two thumb tendons, the APL and EPB, as they pass through a narrow tunnel on the thumb side of the wrist. Thickening of their sheath causes pain during gripping, pinching, and thumb movement.
What causes De Quervain’s tenosynovitis?
It is usually caused by repeated thumb and wrist movements such as lifting a baby, texting, typing, cooking, and racquet sports. Pregnancy, breastfeeding, rheumatoid arthritis, diabetes, and wrist injury also increase the risk, especially in women aged 30 to 50.
What are the symptoms of De Quervain’s tenosynovitis?
Symptoms include pain and swelling near the base of the thumb, pain while gripping or twisting, tenderness over the thumb side of the wrist, and a catching feeling during thumb movement. Pain may spread into the thumb or up the forearm.
What is the Finkelstein test?
The Finkelstein test is a simple clinical test for De Quervain’s. You tuck your thumb into your palm, close your fingers over it, and bend your wrist toward the little finger. Sharp pain on the thumb side of the wrist suggests the condition.
Why is De Quervain’s common in new mothers?
New mothers repeatedly lift babies with their thumbs spread wide, which overloads the thumb tendons. Hormonal fluid changes during pregnancy and breastfeeding add to the problem. That is why the condition is often called mommy thumb or mother’s wrist.
Can De Quervain’s tenosynovitis go away on its own?
Mild cases can settle with rest and activity changes over a few weeks, and postpartum cases often improve after breastfeeding ends. Many patients, however, need a splint, medicines, or an injection. Ignoring symptoms usually makes the condition last longer.
How long should I wear a De Quervain’s splint?
A thumb spica splint is usually worn for four to six weeks, often day and night at first, then mainly during activities and sleep. Consistent use is important. Your doctor will advise when to reduce splint wear as pain improves.
Does a steroid injection work for De Quervain’s?
Yes. A corticosteroid injection into the tendon sheath is one of the most effective treatments and gives good relief in a large share of patients. Some need a second injection. Repeated injections are avoided because they may weaken the tendons.
When is surgery needed for De Quervain’s tenosynovitis?
Surgery is considered when pain continues for several months despite splinting, activity changes, medicines, and one or two injections. De Quervain’s release opens the tendon tunnel through a small incision and is usually performed as a day-care procedure.
How long is recovery after De Quervain’s release surgery?
Stitches are removed in about 10 to 14 days. Most patients resume light hand use within a few days and return to normal activities in four to six weeks. Full grip strength usually returns within two to three months.